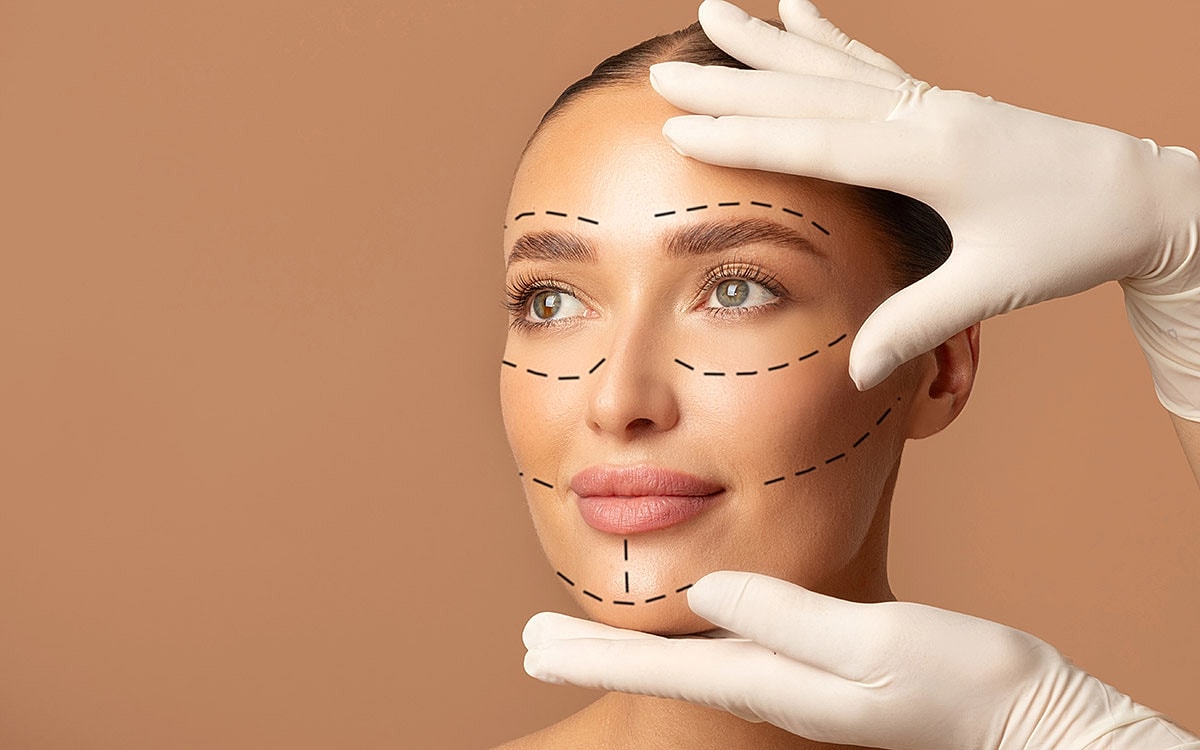
A neck lift treats the neck and jawline: platysma bands, submental fullness, and loose skin below the jaw. A facelift treats the midface and jowls and almost always includes neck work because the two regions share tissue. Isolated neck lifts suit a narrower group than most patients expect. Technique and deep neck anatomy determine what is actually possible.
Most people searching for facelift vs. neck lift believe they are choosing between two separate operations. In practice, they are choosing how far up the same continuous sheet of tissue the surgery needs to travel, because the muscles in your neck and over your cheek are connected.
That connection is why the question gets answered at an exam rather than online. At The One Plastic Surgery Center in Newport Beach, board-certified plastic surgeon Dr. Siamak Agha looks at where the laxity begins, not only where it bothers you. A patient convinced the problem is purely her neck sometimes has jowling that a neck procedure cannot reach, and occasionally the reverse is true.
What follows is a walk through the anatomy first, then the operations, then what each asks of you in recovery. The aim is not to talk you into either one, but to explain why surgeons recommend what they recommend.
Why the Neck Ages on Its Own Schedule
The neck often looks older than the face because more things go wrong in it at once. Skin loses elasticity, fat redistributes both above and below the muscle layer, the muscle itself separates, and the angle between chin and neck softens. Each change needs a different fix.
Clinical references on neck rejuvenation describe the platysma as a thin sheet of muscle across the front of the neck. When its medial borders separate from each other, the vertical cords patients call neck bands appear. That same reference distinguishes two fat layers: subdermal fat above the muscle, which liposuction can address, and subplatysmal fat beneath it, which sits near important vessels and nerves and cannot be treated blindly.
Deeper still, the digastric muscles and the submandibular glands sit under the jaw. When either becomes prominent, the fullness reads as a heavy jawline even in a slim patient. Skin tightening does nothing for it.
Meanwhile, the cervicomental angle, the corner where the underside of the chin meets the neck, becomes obtuse with age. That single measurement is what most people are reacting to when they say their profile has changed.
Facelift vs. Neck Lift: Where the Two Operations Overlap
A neck lift addresses the neck and the lower jawline. A facelift addresses the midface, the jowls, and, in nearly every modern version, the neck as well. The overlap is not marketing. It exists because the platysma continues upward as the same fascial layer that a facelift lifts.
The American Society of Plastic Surgeons defines rhytidectomy, the medical term for a facelift, as surgery addressing visible signs of aging in the face and neck, listing loose neck skin and submental fullness among the concerns it treats. ASPS describes a neck lift as treating jowls, fat under the chin, loose neck skin, and muscle banding, while being clear that neither operation changes your fundamental appearance nor stops aging.
The practice's own facelift and neck lift page reflects that reality, describing the neck lift as most often combined with a facelift for complete lower face and neck rejuvenation.
What a Neck Lift Alone Can and Cannot Do
An isolated neck lift works well for a specific patient: someone whose upper face still looks the way they want it to, whose skin still has decent elasticity, and whose concerns sit at or below the jawline. Outside that profile, the operation tends to underdeliver.
Published guidance on platysmaplasty puts a rough age frame on it. The procedure is described as suited to patients roughly 40 to 60 with mild to moderate neck laxity and good skin elasticity, while patients over 60 with significant excess skin typically need liposuction or a facelift in addition. The same reference notes that platysmaplasty is most commonly performed alongside a full facelift rather than alone.
The limits are worth stating plainly. A neck lift does not lift the cheek, does not soften the fold from the nose to the corner of the mouth, and can only pull the jowl so far because the vector of a neck procedure runs differently than a facelift vector. Patients who treat the neck alone when the midface has also descended often feel the result looks unbalanced.
Cleveland Clinic frames the candidate simply as someone with excess neck fat, horizontal neck bands, or loose skin after weight loss and notes results last year rather than forever, influenced by genetics, sun exposure, and smoking.
Deep Plane vs. SMAS: How Technique Changes the Neck
Technique is where the facelift vs. neck lift conversation becomes concrete, because the layer a surgeon works in determines how much of the neck the operation can influence.
An SMAS facelift works with the superficial musculoaponeurotic system, the fibrous layer just under the skin that connects to the platysma. Tightening or removing a strip of that layer repositions the cheek and jowl and produces some improvement below the jaw. The practice's SMAS facelift page describes this repositioning as the core of the traditional approach.
A deep plane technique dissects beneath that layer instead of over it. Surgical literature describes the dissection proceeding below the mobile SMAS and the orbicularis muscle, releasing retaining ligaments so skin and deeper tissue move together as one unit. The same article describes a subplatysmal release over the gonial angle, the mandibular border, and the submandibular gland, which is why a deep plane facelift tends to produce more definition along the jawline than skin tightening alone.
Deep neck work goes further still. A recent review of deep neck surgery within deep plane facelifts describes addressing subplatysmal fat that cannot be corrected through liposuction alone, reducing prominent submandibular glands, and performing selective myotomies of the digastric muscles to refine the contour. That review is equally clear that deeper neck procedures carry increased risk compared with superficial techniques, particularly bleeding.
Adjuncts That Change the Profile More Than You Expect
Two smaller procedures often do disproportionate work on a neck, and both come up regularly in consultation.
Submental liposuction removes the fat layer above the platysma under the chin. It is frequently performed during a neck lift or facelift rather than as a standalone because in an older patient removing fat without addressing skin or muscle can leave the neck looking hollow rather than defined.
Chin projection is the other. A recessed chin makes the neck look fuller than it is, flattening the angle under the jaw regardless of how much fat is removed. The practice's chin augmentation page notes that a recessed chin makes the neck look fleshy and that chin enhancement can be combined with neck contouring to create a crisper angle under the chin.
Choosing between adjuncts and a full operation is less about preference than about which structure is responsible for what you see in the mirror. A photograph in profile usually tells the surgeon more than a description does.
The layer a surgeon works in decides how much of the neck an operation can change.
Facelift vs. Neck Lift: Recovery and the Longer View
Recovery from an isolated neck lift is generally shorter than recovery from a facelift, though the difference is smaller than patients hope. Both involve swelling and bruising that ease over a couple of weeks, both require sleeping with the head elevated, and both restrict heavy lifting and abrupt head turning early on.
Cleveland Clinic notes that muscle tightness after a neck procedure can persist for several months even after the visible swelling settles and lists bleeding, infection, altered skin sensation, and poor wound healing among the risks. Published platysmaplasty guidance adds injury to the major auricular nerve and persistent banding to the list, noting that most nerve injuries resolve on their own with observation.
A facelift asks for more time because more tissue is elevated, and deep plane and deep neck work extends that further. The trade is reached. The longer operation addresses structures that a shorter one cannot, which is precisely why staging or limiting the procedure is sometimes the safer recommendation for a given patient.
Neither operation pauses aging. Both reset a starting point, and how long that reset holds depends on skin quality, sun exposure, smoking, and weight stability as much as on surgical technique.
Key Takeaways
- A neck lift treats the neck and lower jawline, while a facelift treats the midface and jowls and usually includes neck work.
- Platysma bands, subplatysmal fat, prominent submandibular glands, and a soft cervicomental angle each require different techniques.
- Isolated neck lifts suit patients with good skin elasticity and an upper face they are happy with, often roughly between 40 and 60.
- Deep plane and deep neck techniques reach structures that SMAS work and liposuction cannot, but they carry a higher associated risk.
- Chin projection and submental fat both affect the neck profile and are often addressed alongside the main procedure.
Results and candidacy vary from patient to patient. Only an in-person consultation with a board-certified plastic surgeon can determine whether a facelift, a neck lift, or a combined approach is appropriate for you.
Matching the Operation to the Anatomy
The facelift vs. neck lift question usually resolves once someone examines where your laxity actually starts. If it begins at the jawline and your midface still looks like itself, a neck procedure may be exactly right. If the cheek has descended and the jowl has formed, a neck lift will leave part of the concern untouched.
The honest version of this conversation covers what each operation cannot do, which structures contribute to your profile, and what recovery actually asks of you.
Ready to find out whether a facelift, a neck lift, or a combination fits your anatomy and your goals? Schedule a consultation with board-certified plastic surgeon Dr. Siamak Agha at The One Plastic Surgery Center in Newport Beach to review your options in person.
Frequently Asked Questions
Can I have a neck lift without a facelift?
Yes, and it is a reasonable choice for patients whose upper face still looks the way they want and whose skin retains excellent elasticity. Published guidance describes isolated platysmaplasty as best suited to patients with mild to moderate laxity, often roughly between 40 and 60. Patients with significant excess skin usually need a facelift component as well.
Will a neck lift get rid of my jowls?
Partly. A neck lift improves the lower jawline and can soften early jowling, but jowls form from the descent of midface tissue, which a neck procedure reaches only to a limited degree. When jowling is the main concern, surgeons typically recommend a facelift or a combined approach instead.
What causes fullness under my jaw if I am not overweight?
Several structures can be responsible. Subplatysmal fat beneath the neck muscle, prominent digastric muscles, and enlarged or descended submandibular glands all create fullness that liposuction cannot correct. Identifying which one applies to you requires an in-person examination rather than a photograph.
Is a deep plane facelift better for the neck than an SMAS facelift?
A deep plane dissection releases tissue beneath the SMAS layer and extends over the jaw border and submandibular region, which generally allows more change in the neck and jawline. It is also a longer operation with a different risk profile. The right technique depends on your anatomy and health history, not on which name sounds more advanced.
How much longer is facelift recovery compared with a neck lift?
A neck lift is usually the shorter recovery of the two, though both involve roughly a couple of weeks of visible swelling and bruising and several weeks of activity restrictions. Deep plane and deep neck procedures generally extend that timeline further because more tissue is elevated. Muscle tightness in the neck can persist for months after swelling resolves.